On this page
- Why daily hydration matters and how water balance works
- How to use this calculator and read every output
- Inside the formula: the 0.033 L/kg rule and rounding
- Exercise, sweat rate variability, heat, humidity, and altitude
- Food moisture, coffee, tea, milk, and total water intake
- Reference intakes from international health authorities
- Three step-by-step worked hydration examples
- Practical self-monitoring: thirst, urine colour, and daily pacing
- Clinical safety, hyponatraemia, medical conditions, and urgent warning signs
- Common hydration mistakes to avoid
- Where this tool stops and how your data is handled
- Sources and clinical guidelines
Why daily hydration matters and how water balance works
Water accounts for roughly 50 to 65 per cent of an adult's total body weight and sits at the centre of nearly every physiological system. Inside the bloodstream, water maintains plasma volume so the heart can pump oxygenated blood to working muscles, kidneys, and brain tissue without excessive cardiovascular strain. Across skin surfaces, evaporative sweating dissipates metabolic heat so core temperature stays safely near 37 degrees Celsius during warm weather or physical effort. In the kidneys, adequate renal blood flow and urine volume allow dissolved metabolic waste products—such as urea, creatinine, uric acid, and excess dietary sodium—to be filtered and excreted efficiently without forming concentrated mineral crystals.
Even mild acute dehydration—often defined in sports and clinical physiology studies as an unreplaced body-water loss equal to 1.5 to 2 per cent of body mass—can noticeably increase perceived exertion, trigger dull tension headaches, slow working memory and vigilance, and accelerate heart rate during physical work (a phenomenon known as cardiovascular drift). Yet human hydration is governed by dynamic feedback loops rather than a fragile single quota. When blood concentration (plasma osmolality) rises by even 1 to 2 per cent, specialised osmoreceptors in the hypothalamus trigger thirst and release antidiuretic hormone (vasopressin), instructing the kidneys to conserve water and produce smaller volumes of darker, more concentrated urine. When you drink more fluid than you currently need, vasopressin falls and healthy kidneys excrete the surplus as pale, dilute urine.
Understanding daily hydration starts with seeing water as a continuous input-and-output ledger. In a temperate environment on a rest day, a typical adult turns over roughly 2.2 to 2.8 litres of water every 24 hours. Beverages supply about 70 to 75 per cent of that inflow, moisture locked inside solid foods supplies roughly 20 to 25 per cent, and a further 250 to 300 millilitres of endogenous "metabolic water" is generated directly inside your cells as carbohydrates, fats, and proteins are oxidised for energy. On the output side, urine accounts for the largest share, followed by insensible evaporation from the lungs while breathing, basal skin perspiration, and a small amount of water lost in stool.
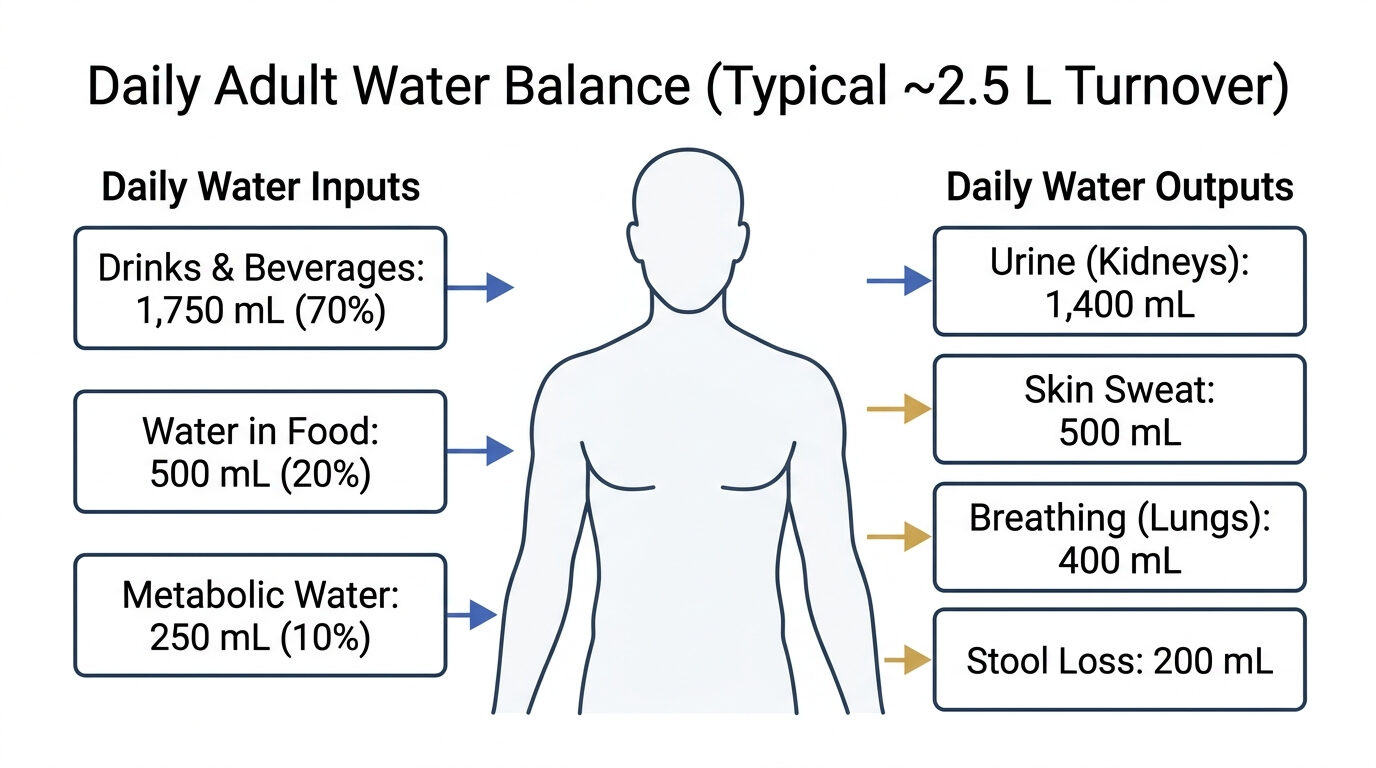
Because body mass, ambient temperature, humidity, physical activity, dietary water content, altitude, and health status all shift those input and output arrows, no calculator can hand you a clinically exact prescription. Instead, this tool calculates a transparent, weight-scaled starting point for total daily water so you can plan your routine sensibly and fine-tune intake using thirst, daytime urine colour, and professional medical guidance where needed.
How to use this calculator and read every output
The calculator is intentionally straightforward so you can model an ordinary weekday or training day in seconds without creating an account. Nothing runs automatically on page load; enter your own details or select one of the quick example presets, then click Calculate water goal.
- Body weight (kg): Enter your current adult body weight in kilograms between 25 and 500 kg. If you track your weight in pounds, divide pounds by 2.2046 to convert to kilograms (for example, 154 lb ÷ 2.2046 = 69.9 kg; you can also convert units with the Unit Converter). This tool is designed for adults and older adolescents rather than infants or young children, whose paediatric fluid requirements follow distinct clinical formulas.
- Daily exercise (minutes): Enter the duration of purposeful moderate-to-vigorous physical activity on a typical day, from 0 to 600 minutes. Leave the field blank or enter 0 for a sedentary rest day. Do not include casual indoor standing or slow household movement here; reserve exercise minutes for brisk walking, running, cycling, gym training, manual outdoor labour, or active sport.
- Typical climate: Choose Temperate or usual (+0.00 L) if you spend most of your day in mild weather or indoor climate-controlled rooms, or select Hot or humid (+0.50 L) if you regularly commute, work, or live in warm ambient heat or high tropical humidity without full-day air conditioning.
- Preferred display unit: Select whether you want the results card to show all three units side by side (litres, millilitres, and 500 mL bottles), highlight Litres only, or display your goal in 500 mL bottles only for practical bottle-counting during work or classes.
Once calculated, the results panel presents four coordinated layers: your headline total-water estimate, unit conversions (including standard 500 mL bottles rounded to the nearest half bottle, such as 4.5 or 7.0 bottles), an itemised arithmetic breakdown showing exact millilitres alongside two-decimal litre figures, and four sanity checks comparing your result against typical adult reference ranges (2.0 to 4.0 litres) and a general 5.0-litre upper planning ceiling. If you want to turn your calculated litre target into timed hourly drinking intervals across your waking day, pair your figure with the Hydration Reminder Calculator.
Inside the formula: the 0.033 L/kg rule and rounding
Popular articles still repeat the old "drink eight 8-ounce glasses (about 1.9 litres) of water every day" slogan, despite decades of clinical literature showing that a single flat volume ignores body size completely. A 50-kilogram office worker in a cool city and a 98-kilogram warehouse supervisor working in coastal heat do not share the same basal metabolic water turnover or body surface area. To scale your baseline sensibly with body mass, this calculator starts with a widely used dietetic planning heuristic of 33 millilitres of total water per kilogram of body weight per day (0.033 L/kg), which sits near the middle of the standard 30 to 35 mL/kg clinical nutrition reference band for healthy adults.
Notice two mathematical details in how the calculator handles precision so the numbers never contradict one another:
- Full-precision addition before rounding: Each component—base water, exercise allowance, and climate allowance—is added at full decimal precision in millilitres before the final litre figure is rounded to two decimal places. For example, at 72 kg with 45 minutes of exercise in a hot climate, base water is exactly 2.376 L (2,376 mL) and exercise adds 0.525 L (525 mL). Individually rounded to two decimals, those rows read 2.38 L and 0.53 L, which would appear to add up to 3.41 L with a 0.50 L climate allowance, whereas the true unrounded sum is 2.376 + 0.525 + 0.500 = 3.401 L (3,401 mL), which rounds accurately to 3.40 L. Displaying both the two-decimal litre figure and exact millilitres in the breakdown keeps that rounding completely transparent.
- Nearest half-bottle rounding: Nobody measures 6.82 of a reusable water bottle across a workday. The 500 mL bottle counter divides your unrounded litre total by 0.50 L and rounds to the nearest 0.5 bottle (so 2.31 L becomes 4.5 bottles, and 3.401 L becomes 7.0 bottles), giving you a practical visual target without false precision.
Keep one physiological limitation of weight-based rules in mind: skeletal muscle tissue is roughly 73 per cent water by weight, whereas adipose (fat) tissue holds only about 10 per cent water. Consequently, two people who both weigh 105 kg—one a lean rugby forward and the other a sedentary adult carrying higher body fat—have noticeably different active lean tissue and metabolic water turnover. At higher body weights accompanied by higher body fat percentage, multiplying total scale weight by 0.033 L/kg can slightly overestimate resting fluid needs. If you want context on body composition or energy expenditure alongside hydration, see the Body Fat Calculator and Daily Calorie Needs Calculator.
Exercise, sweat rate variability, heat, humidity, and altitude
During physical activity, contracting skeletal muscles convert roughly 75 to 80 per cent of expended metabolic energy into heat rather than mechanical motion. To keep core body temperature within safe bounds, sympathetic nerves stimulate eccrine sweat glands across the skin, and faster, deeper breathing increases water vapour lost from the respiratory tract. This calculator adds 0.35 litres (350 mL) per 30 minutes of exercise—equivalent to 0.70 litres per hour—which sits near the middle of general sports-medicine allowances (0.4 to 0.8 L/hr) for recreational walking, jogging, cycling, or gym workouts in moderate conditions.
Real-world human sweat rates, however, vary wider than almost any other physiological trait. Measured sweat losses in published sports science research span from 0.3 litres per hour during gentle indoor exercise up to 2.0 to 2.5 litres per hour during intense team sports, distance running, or heavy manual labour in hot, humid weather. Four environmental and personal factors drive that gap:
- Relative humidity vs. dry heat: Cooling comes from sweat evaporating off skin, not merely dripping onto clothing or pavement. In dry desert or inland heat (such as Gaborone, Windhoek, or Kano in the dry season), sweat evaporates rapidly so you may not even notice damp skin while losing substantial fluid. In humid coastal climates (such as Lagos, Dar es Salaam, Mombasa, or Durban), high water vapour pressure in the air slows evaporation, forcing the body to secrete even larger volumes of sweat to achieve the same cooling effect.
- Heat acclimatisation and fitness: After 7 to 14 days of repeated exposure to exercise in warm conditions, the body adapts by expanding plasma volume, starting to sweat earlier at a lower core temperature, increasing total sweat output, and reabsorbing more sodium in sweat ducts so sweat becomes less salty. Well-trained, heat-acclimatised athletes therefore need more water per hour in the heat than unacclimatised beginners working at the same relative effort.
- High altitude: Living, hiking, or training at moderate-to-high elevation (roughly 1,500 to 2,500+ metres above sea level, including cities and training plateaus across East and Southern Africa) accelerates breathing in drier, lower-pressure air and triggers mild altitude-induced diuresis in the first days of exposure, raising baseline fluid losses even when temperatures feel crisp and cool.
- Clothing and airflow: Heavy protective workwear, helmets, synthetic uniforms, or indoor gyms with poor fan airflow trap heat around the skin microclimate and raise sweat loss well above outdoor breezy conditions at the same air temperature.
| Activity & Environment Profile | Typical Sweat Rate | Calculator Setting | Practical Hydration & Electrolyte Strategy |
|---|---|---|---|
| Light-to-moderate indoor gym, yoga, or brisk cool-weather walk | 0.30 to 0.55 L/hr | 0.70 L/hr (Temperate) | Plain water around the session and normal meals easily cover fluid and electrolyte losses. |
| Moderate running, cycling, or circuit class in mild weather | 0.60 to 0.90 L/hr | 0.70 L/hr (Temperate) | Calculator exercise allowance matches typical losses closely; sip before and after training. |
| Vigorous team sport (football, rugby, basketball) or warm-weather run | 0.90 to 1.40 L/hr | 0.70 L/hr + 0.50 L Hot | For sessions over 60–90 minutes, include sodium (300–600 mg/hr via sports drink or salted snack post-session). |
| Multi-hour outdoor manual work, farming, construction, or hot-weather endurance | 1.20 to 2.00+ L/hr | Floor estimate only | Treat calculator output as a minimum floor; measure personal sweat rate or drink steadily to thirst alongside salted meals. |
How to check your personal 1-hour sweat rate at home: If you train or work hard in the heat and want to know whether 350 mL per 30 minutes under- or overestimates your personal sweat loss, weigh yourself nude or in dry minimal clothing immediately before a 60-minute session, then towel dry and weigh yourself in the exact same dry clothing afterward. Every 0.1 kg (100 g) of body weight lost equals roughly 100 mL of sweat loss, plus any millilitres of fluid you drank during the hour (minus any urine passed). Aim to keep single-session body-weight loss under 2 per cent during workouts and replace roughly 125 to 150 per cent of net post-exercise deficit gradually over the next 2 to 4 hours with meals and fluids, since kidneys continue producing obligatory urine while you rehydrate.
Food moisture, coffee, tea, milk, and total water intake
One of the most frequent sources of anxiety around hydration calculators is confusing total daily water with plain bottled or tap water. Both the National Academies (NASEM) and the European Food Safety Authority (EFSA) define daily water reference intakes as total water from all beverages plus moisture contained in solid foods. For most mixed diets, food contributes 20 to 30 per cent of daily water—roughly 500 to 800 millilitres per day—and diets built around fresh fruits, cooked leafy greens, stews, soups, porridges, and boiled grains or tubers can supply close to 1.0 litre from meals alone.
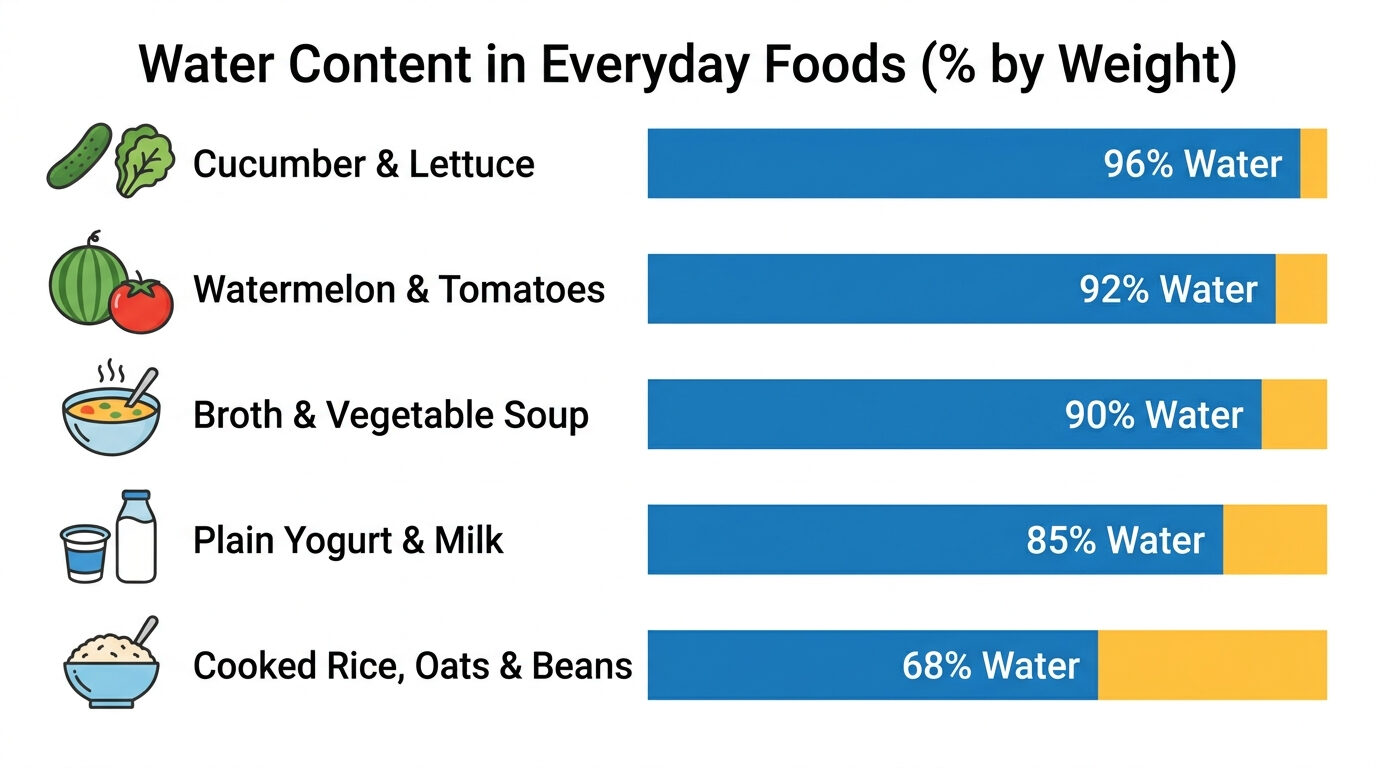
Consider what an ordinary day of eating already contributes before you count plain drinking water: a morning bowl of cooked oats or maize porridge made with water or milk holds around 180 to 220 mL of water; an orange or slice of watermelon at midday adds 130 to 180 mL; a dinner plate with 150 g of cooked rice or beans alongside vegetable stew or soup supplies another 250 to 350 mL. Conversely, days dominated by dry ultra-processed foods—crackers, crisps, roasted nuts, dry bread, and cured or grilled meats (which sit between 2 and 40 per cent moisture and carry higher dietary sodium and protein solute loads)—contribute very little food water and genuinely require more drinking fluid to compensate.
Beverage choices also follow clear physiological evidence rather than folklore:
- Plain potable water: Zero calories, zero added sugars, gentle on teeth, and inexpensive when safe tap, filtered, or boiled water is available—making it the best default beverage for the bulk of the day.
- Tea and coffee: Controlled fluid-balance trials comparing moderate coffee consumption (roughly 3 to 4 cups providing ~250 to 300 mg of caffeine) against equal volumes of plain water in habitual caffeine drinkers show virtually identical 24-hour urine output and hydration markers. Only very large acute doses of caffeine (above 500 mg, especially in people who rarely consume caffeine) trigger a meaningful short-term diuretic loss. Unsweetened black, green, or herbal teas and moderate coffee count toward your daily fluid goal.
- Milk and fermented dairy: Skimmed and whole milk are roughly 87 to 90 per cent water and contain natural sodium, potassium, lactose, and protein, which slow stomach emptying and blunt rapid urine spikes—giving milk a high clinical Beverage Hydration Index, though its calorie content should fit your overall nutrition goals.
- Sugar-sweetened drinks and fruit juices: Soft drinks, sweetened squashes, and energy drinks hydrate in a literal fluid sense, but high concentrations of free sugars contribute to excess calorie intake, dental caries, and poor glycaemic control, while hypertonic high-sugar drinks can briefly draw water into the gut lumen during intense exercise and cause stomach cramping.
- Alcoholic beverages: Alcohol directly inhibits vasopressin release in the pituitary gland. Spirits, wine, and standard-strength beer (typically 4 per cent ABV and above) cause net fluid loss rather than net hydration and should never be counted toward your daily water target; alternate alcoholic drinks with plain water.
Reference intakes from international health authorities
Weight-based formulas are helpful personal planning tools, while public health authorities publish population-wide Adequate Intake (AI) benchmarks based on national dietary surveys and urine osmolality studies. Comparing your calculator estimate against these benchmarks helps you see where your body size and lifestyle sit relative to population medians.
| Life Stage & Group | NASEM Total Water (US/Canada) | EFSA Total Water (Europe) | Approx. Beverages Only (75–80%) | Key Context & Notes |
|---|---|---|---|---|
| Adult men (19+ years) | 3.7 L / day | 2.5 L / day | 2.0 to 3.0 L / day | NASEM reflects median US survey intake across varied climates; EFSA links target to desired urine osmolality. |
| Adult women (19+ years) | 2.7 L / day | 2.0 L / day | 1.6 to 2.2 L / day | Covers total water from plain water, tea/coffee, other non-alcoholic drinks, and food moisture. |
| Adolescent boys (14–18 years) | 3.3 L / day | 2.5 L / day | 1.9 to 2.6 L / day | Rapid growth and school sport in warm weather can push sweat losses closer to adult ranges. |
| Adolescent girls (14–18 years) | 2.3 L / day | 2.0 L / day | 1.6 to 1.8 L / day | Needs rise substantially on school athletics or outdoor training days. |
| Pregnancy (all trimesters) | 3.0 L / day | 2.3 L / day | 1.8 to 2.4 L / day | Adds ~300 mL/day above standard female baseline to support plasma expansion and amniotic fluid. |
| Breastfeeding / Lactation | 3.8 L / day | 2.7 L / day | 2.2 to 3.1 L / day | Adds ~600–700 mL/day to offset average daily breast-milk water secretion (~750 mL/day). |
Why is the North American (NASEM) Adequate Intake noticeably higher than the European (EFSA) value—3.7 L versus 2.5 L for men, and 2.7 L versus 2.0 L for women? NASEM derived its Adequate Intake from median self-reported total water consumption in healthy US survey participants, whereas EFSA combined dietary intake data with physiological calculations of the water volume needed to maintain a moderate 24-hour urine osmolality of roughly 500 mOsm/L. Neither figure is a minimum survival threshold or a strict medical target; healthy kidneys maintain normal serum sodium across a wide span of intakes between both benchmarks.
Three step-by-step worked hydration examples
Walking through three distinct profiles shows exactly how the calculator builds its estimate, how food moisture fits into the total, and how to turn the result into a realistic daily habit.
Example 1: 72 kg recreational runner in a hot, humid coastal city
Consider a 72 kg adult living in a warm, humid coastal city who goes for a 45-minute moderate run on most mornings (the third preset button above). Entering 72 kg, 45 minutes, and Hot or humid produces the following step-by-step calculation:
| Component | Formula Applied | Exact Volume (mL) | Displayed Litres |
|---|---|---|---|
| Base water | 72 kg × 0.033 L/kg | 2,376 mL | 2.38 L |
| Exercise allowance | (45 min ÷ 30) × 0.35 L | 525 mL | 0.53 L |
| Climate allowance | Hot or humid setting | 500 mL | 0.50 L |
| Estimated daily total water | Sum of exact mL (3,401 mL) | 3,401 mL | 3.40 L |
Dividing 3.401 litres by 0.50 litres gives 6.802 bottles, which rounds to 7.0 × 500 mL bottles (nearest half bottle). If roughly 20 to 25 per cent of that 3.40 L comes from fruit, cooked grains, and dinner stew (~750 mL), the runner needs around 2.65 L of actual beverages across the day: for example, 350 mL upon waking, 500 mL around and immediately after the morning run, two 500 mL bottles spaced across work hours, a cup of tea (250 mL), and two glasses (550 mL) spread across afternoon and early evening.
Example 2: 58 kg university student on a temperate rest day
Now consider a 58 kg student spending a cool, temperate weekday in lecture halls and the library with no structured workout (0 exercise minutes, Temperate climate):
- Base water: 58 kg × 0.033 L/kg = 1.914 L (1,914 mL), displayed as 1.91 L.
- Exercise & climate allowances: 0 mL + 0 mL = 0.00 L.
- Bottle conversion: 1.914 L ÷ 0.50 L = 3.828, which rounds to 4.0 × 500 mL bottles.
Notice that the first "Plan check" notes that 1.91 L sits slightly under the general 2.0 to 4.0 L adult window. For a healthy 58 kg adult on a sedentary cool day, 1.91 to 2.00 L of total water aligns closely with EFSA's 2.0 L female reference value. With ~450 mL coming from meals, drinking roughly 1.45 to 1.55 L of beverages (about three 500 mL bottles or six 250 mL cups of water, tea, or milk) comfortably meets daily needs without unnecessary bathroom trips during exams.
Example 3: 88 kg outdoor field technician with 90 minutes of heavy physical effort in heat
Consider an 88 kg technician or amateur footballer active for 90 minutes in hot weather (88 kg, 90 minutes, Hot or humid):
- Base water: 88 kg × 0.033 L/kg = 2.904 L (2,904 mL, displayed as 2.90 L).
- Exercise allowance: (90 ÷ 30) × 0.35 L = 1.050 L (1,050 mL, displayed as 1.05 L).
- Climate allowance: 0.500 L (500 mL, displayed as 0.50 L).
- Total estimate: 2.904 + 1.050 + 0.500 = 4.454 L (displayed as 4.45 L, 4,454 mL, or 9.0 × 500 mL bottles).
At 4.45 L, pacing and electrolytes become essential. Drinking 4+ litres safely requires spreading fluids steadily across 15 waking hours (averaging 250 to 350 mL per hour during normal hours and 500 to 700 mL per hour around heavy heat work) and eating normal salted meals—or adding an electrolyte solution during the 90-minute hot session—so sodium lost in salty sweat is replaced alongside water. You can also check approximate workout energy expenditure for the session using the Calorie Burn Calculator.
Practical self-monitoring: thirst, urine colour, and daily pacing
Instead of tracking every sip with anxiety, combine your calculated starting number with two simple biological checks across the day: thirst and daytime urine colour. Urine gets its natural yellow tint from urochrome, a pigment produced during normal haemoglobin breakdown and excreted at a fairly steady daily rate. When body water is plentiful, urochrome is diluted into pale straw or light yellow urine; when body water drops and vasopressin concentrates urine, the same pigment deepens to dark yellow or amber.

Keep four practical nuances in mind when reading urine colour and structuring your day:
- Check mid-day voids, not first-morning urine: Overnight vasopressin release naturally concentrates urine while you sleep so your bladder does not wake you repeatedly. Slightly darker urine on your first morning trip is normal; judge hydration from your second and subsequent daytime voids.
- Account for harmless colour confounders: Multivitamins and B-complex supplements containing riboflavin (vitamin B2) turn urine bright fluorescent yellow for several hours regardless of hydration status. Beetroot, blackberries, and rhubarb can add a pink or reddish hue, while medications such as rifampicin (orange-red), phenazopyridine (deep orange), nitrofurantoin (rust-yellow), or diuretics alter colour or volume independently of true body-water balance.
- Nearly clear is not the ultimate goal: Passing completely transparent, water-clear urine every hour usually means you are drinking well past physiological need and flushing fluid straight through your kidneys. Pale straw to light lemonade yellow (Bands 2 to 3) signals comfortable euhydration.
- Front-load gently and taper before sleep: Having 250 to 350 mL of water within the first hour of waking, keeping a refillable 500 mL bottle at your desk, drinking naturally with meals, and tapering large drinks 90 to 120 minutes before bedtime protects uninterrupted sleep while meeting your daily total effortlessly.
Clinical safety, hyponatraemia, medical conditions, and urgent warning signs
Important Medical Disclaimer: All figures produced by this calculator and discussed in this article are general educational estimates for healthy adults. They do not constitute medical advice, clinical diagnosis, or individualised treatment. Always follow fluid and electrolyte instructions from a licensed physician, pharmacist, midwife, or registered dietitian, and seek urgent medical care immediately if severe symptoms develop.
When more water becomes dangerous: hyponatraemia
Healthy adult kidneys at rest can excrete roughly 0.7 to 1.0 litres of free water per hour, and during prolonged physical stress, pain, nausea, or multi-hour endurance events, non-osmotic vasopressin release can cut maximum renal water excretion well below 0.5 litres per hour. Drinking large volumes of plain water faster than your kidneys and sweat glands remove it dilutes blood sodium concentration below 135 mmol/L—a potentially life-threatening condition called hyponatraemia (including exercise-associated hyponatraemia in marathoners, hikers, and military trainees who drink aggressively at every water station).
When extracellular sodium drops rapidly, osmotic pressure drives water into cells, including brain cells enclosed inside the rigid skull. Early symptoms—nausea, abdominal fullness or sloshing, headache, puffiness in the fingers (tight rings or watchbands), and malaise—can easily be mistaken for dehydration, tempting a person to drink even more plain water and worsen the crisis. Never force several litres of water in a short window to "catch up" on a daily target or "detox", and during endurance events, drink to thirst rather than drinking ahead of weight loss.
Medical conditions and medications that change fluid rules
General body-weight hydration calculators must not be used to override clinical guidance in any condition that alters kidney filtration, circulatory volume, or electrolyte regulation:
- Fluid-restricted conditions: Advanced chronic kidney disease (stages 4–5 or dialysis), congestive heart failure, liver cirrhosis with ascites or peripheral oedema, and syndrome of inappropriate antidiuretic hormone secretion (SIADH) frequently require strict clinician-prescribed fluid ceilings (sometimes 1.0 to 1.5 litres per day from all liquids) to prevent dangerous fluid overload, pulmonary congestion, or severe hyponatraemia.
- Conditions requiring targeted higher or specialised hydration: Patients with a history of kidney stones (nephrolithiasis) are often advised by urologists to drink enough fluid to produce at least 2.0 to 2.5 litres of actual urine per day (unless contraindicated), while uncontrolled diabetes mellitus causes osmotic urination and heightened thirst that require blood-glucose treatment rather than calculator guesswork.
- Acute fever, vomiting, and diarrhoea: Fever increases evaporative water loss, while acute gastroenteritis drains water alongside sodium, chloride, potassium, and bicarbonate. Replacing heavy diarrhoeal losses with plain water alone risks electrolyte depletion. World Health Organization (WHO) reduced-osmolarity Oral Rehydration Salts (ORS) use precise sodium-to-glucose ratios to activate intestinal co-transporters and restore intravascular volume safely; always mix ORS packets strictly as directed rather than guessing homemade salt spoons.
- Fluid-modifying medications: Loop and thiazide diuretics, SGLT2 inhibitors (used in diabetes, heart failure, and kidney disease), lithium (where dehydration rapidly elevates blood lithium to toxic levels), carbamazepine, oxcarbazepine, SSRIs/SNRIs (which can predispose older adults to SIADH), and NSAIDs taken during prolonged heat exertion all require medication-specific hydration guidance from your doctor or pharmacist.
When to seek urgent medical care
Do not rely on any online calculator if warning signs of severe dehydration, heat illness, or acute water intoxication appear. Seek prompt or emergency medical evaluation if you or someone in your care experiences:
- Confusion, disorientation, slurred speech, unusual drowsiness, agitation, fainting, or seizures.
- Dizziness or lightheadedness when standing up, accompanied by a rapid or weak resting pulse.
- Very little or no urination for 8 to 12 hours, or persistently dark amber, tea-coloured, or bloody urine.
- Persistent vomiting or inability to keep small sips of oral rehydration fluid down for more than 12 to 24 hours, or severe watery/bloody diarrhoea.
- High fever, hot flushed or clammy skin, muscle spasms, or suspected heat exhaustion / heatstroke after sun or workplace heat exposure.
- Rapid weight gain, swollen hands/face, worsening throbbing headache, or nausea/vomiting after drinking large quantities of plain water.
Common hydration mistakes to avoid
Treating the calculated figure as an exact daily mandate. Two thousand five hundred millilitres and two thousand seven hundred millilitres are practically indistinguishable for healthy kidneys. Day-to-day swings of 200 to 400 millilitres based on meals, weather, and thirst are completely normal.
Forgetting that meals supply 20 to 30 per cent of total water. Drinking 3.2 litres of plain bottled water on top of fruit, soup, tea, and cooked meals pushes total water above 4.0 litres unnecessarily.
Selecting the Hot or humid climate option for indoor air-conditioned days. Even if you live in a warm country, spending 22 hours a day between air-conditioned home, car, and office resembles a temperate thermal load. Reserve the +0.50 L climate setting for days when heat or humidity meaningfully affects your body.
Discarding tea, coffee, and milk from your count. Moderate tea, coffee, and milk contribute real water. Limiting sugary soft drinks makes sense for metabolic and dental health, not because plain water is the only liquid your gut absorbs.
Chugging a two-litre deficit late in the evening. Gulping a huge volume at 9 p.m. triggers rapid diuresis (the bolus response), fragments sleep with overnight trips to the bathroom, and is uncomfortable—or hazardous at extreme volumes.
Replacing heavy diarrhoea or multi-hour heat sweat with plain water alone. When large amounts of sodium and potassium are lost through prolonged heavy sweating or gastrointestinal illness, electrolytes matter alongside water.
Overriding a doctor's fluid plan. Anyone managing kidney, heart, liver, or sodium disorders must follow their clinician's prescribed range rather than a weight-based web calculator.
Where this tool stops and how your data is handled
This calculator models a practical daily total-water starting estimate from three inputs: adult body weight (25 to 500 kg), daily exercise duration (0 to 600 minutes), and a two-tier climate setting. It cannot measure your personal sweat rate or sweat sodium concentration, does not distinguish lean muscle mass from adipose tissue, does not inspect your daily diet or dietary sodium/protein load, is not suitable for infants or young children, and cannot account for pregnancy, lactation, acute illness, chronic disease, or prescription medications. Pair it with common sense, thirst, daytime urine observation, and professional medical guidance whenever health conditions apply.
Regarding privacy and browser storage: all core hydration arithmetic runs locally inside your browser tab using client-side JavaScript, and your inputs are never saved to a remote database. Your browser's localStorage is used locally on your own device only for optional convenience features—remembering your cookie banner preference, saved favourite tools, and local on-device history inside the Health Progress tracker (which you can clear with one click at any time). Only if you actively press the optional Get AI insight button does your browser send a one-time summary payload (weight band, exercise minutes, climate choice, and calculated litre figures) to /api/ai-insight to generate the brief pacing note.
Sources and clinical guidelines
- National Academies of Sciences, Engineering, and Medicine (Institute of Medicine). Dietary Reference Intakes for Water, Potassium, Sodium, Chloride, and Sulfate. nationalacademies.org
- European Food Safety Authority (EFSA) Panel on Dietetic Products, Nutrition, and Allergies. Scientific Opinion on Dietary Reference Values for Water (EFSA Journal 2010;8(3):1459). efsa.europa.eu
- World Health Organization (WHO). Oral Rehydration Salts: Production of the New ORS & Water, Sanitation and Hygiene Guidelines. who.int
- Centers for Disease Control and Prevention (CDC). Water and Healthier Drinks. cdc.gov
- National Health Service (NHS UK). Water, Drinks and Nutrition (Eat Well Guidelines). nhs.uk
- American College of Sports Medicine (ACSM). Position Stand: Exercise and Fluid Replacement (Sawka et al., Medicine & Science in Sports & Exercise). acsm.org