On this page
- What this calculator estimates and how to enter accurate inputs
- Hormones and physiology across the four menstrual cycle phases
- Inside the six-day fertile window: conception odds and gamete survival
- Exact calendar math, Cycle Day 1 indexing, and why ovulation moves
- Three step-by-step worked cycle examples
- Confirming ovulation at home: cervical mucus, LH strips, and BBT
- Irregular cycles, PCOS, thyroid shifts, postpartum, and perimenopause
- Why calendar dates are not contraception—and how FABMs differ
- Common tracking mistakes and luteal vs early pregnancy symptoms
- Clinical limitations, fertility timelines, and urgent warning signs
- Authoritative clinical sources and guidelines
What this calculator estimates and how to enter accurate inputs
Understanding when ovulation happens—and why it rarely sits permanently on the fourteenth day of the month—takes much of the guesswork out of menstrual tracking and conception planning. This calculator takes four straightforward inputs about your menstrual pattern and maps them onto specific calendar dates: your estimated ovulation day, the clinical six-day fertile window leading up to and including ovulation, the three peak conception days inside that window, a 24-hour post-ovulation egg-viability buffer day, your next expected period start date, and the remaining non-fertile calendar intervals.
Every output is a mathematical projection built from the backward-luteal calendar model, not a direct biological sensor. Because a calendar calculator can only be as reliable as the baseline figures fed into it, getting the four inputs right makes a substantial difference to the usefulness of your estimate:
- First day of last period (Cycle Day 1): Enter the calendar date on which full, bright-red menstrual flow began—meaning bleeding substantial enough to need a pad, tampon, menstrual cup, or period underwear. Do not enter the date of light brown or pink pre-menstrual spotting a day or two before flow starts, and do not enter the date your period ended. In fertility clinics, if full flow begins late at night after you have gone to bed (commonly defined as after 21:00 or midnight), the following calendar day is recorded as Cycle Day 1; choose one cutoff rule and apply it consistently.
- Average cycle length (21 to 45 whole days): A single menstrual cycle runs from Cycle Day 1 of one period up to and including the final day before your next full period begins. Rather than assuming 28 days because textbooks repeat that number, average the lengths of your last three to six natural (non-hormonal) cycles. For instance, if your last four cycles lasted 29, 31, 30, and 30 days, entering 30 days reflects your personal follicular rhythm far better than 28.
- Period bleeding duration (1 to 14 whole days): Count the days of active menstrual flow from Cycle Day 1 until bleeding stops. Most ovulatory adult periods last between 3 and 7 days. Entering your true bleeding length allows the calculator to flag short-cycle overlaps—situations where fertile sperm-supportive days begin before menstrual bleeding has completely finished.
- Assumed luteal phase (10 to 16 days, default 14): The luteal phase is the post-ovulatory interval starting the day after ovulation (1 day past ovulation, or 1 DPO) through the final day before your next period starts. If you have never tracked ovulation with urinary luteinising hormone (LH) strips or morning basal body temperature (BBT), keep the population default of 14 days. If prior tracking has consistently shown that your period arrives 12 or 13 days after ovulation, selecting that figure shifts your estimated fertile window forward by one or two crucial days.
Hormones and physiology across the four menstrual cycle phases
A menstrual cycle is not merely a uterine event; it is a tightly coordinated conversation along the hypothalamic-pituitary-ovarian (HPO) axis. Pulsatile gonadotropin-releasing hormone (GnRH) from the hypothalamus prompts the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinising hormone (LH), while maturing ovarian follicles and the post-ovulatory corpus luteum respond by secreting estradiol, progesterone, and inhibin hormones that remodel the uterine lining (endometrium) and cervical mucus.
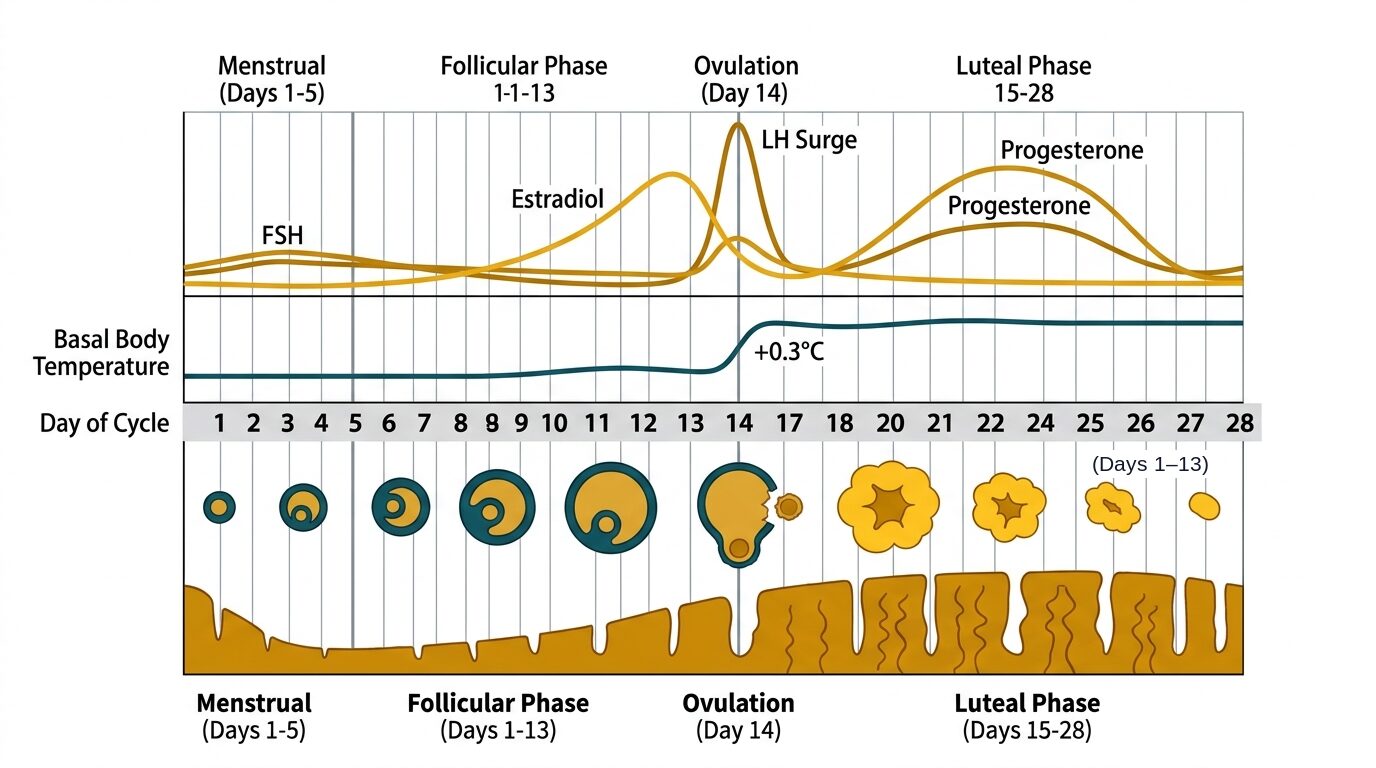
Note that the menstrual phase and early follicular phase overlap on Cycle Days 1 to 5: while the uterus sheds last month's functional lining, the ovaries are already recruiting a fresh cohort of follicles for the new cycle. Separating the four phases clarifies what is happening inside the body on each part of the timeline:
| Cycle Phase | Typical Timing | Dominant Hormones | Ovarian & Uterine Activity | Observable Body Clues |
|---|---|---|---|---|
| Menstrual | Cycle Days 1 to 5 (usual range 3–7 days) | Low estradiol, low progesterone, early rise in FSH | Functional endometrial layer sheds; 20 to 80 mL total blood and tissue loss while small antral follicles begin recruitment. | Active red menstrual bleeding; uterine prostaglandin cramping on Days 1–2; resting BBT drops back to lower follicular baseline. |
| Follicular (Proliferative) | Cycle Day 1 up to ovulation (most variable phase) | FSH early, then steeply rising estradiol from the dominant follicle | One dominant Graafian follicle outgrows peers (~18–24 mm before rupture); estradiol rebuilds a thick, vascular proliferative endometrium. | Dry or sticky days immediately post-period, transitioning to creamy and then clear, slippery, stretchy cervical mucus as estradiol peaks. |
| Ovulation | Mid-cycle event (~24–36 h after LH surge onset) | Sustained high estradiol flips pituitary feedback, causing a sharp LH surge | Dominant follicle wall enzymatically softens and releases a mature oocyte into the fallopian tube fimbriae; egg survives 12 to 24 hours. | Peak slippery raw-egg-white mucus; positive urinary LH strip; cervix feels soft, high, and slightly open; mild one-sided pelvic twinge in some cycles. |
| Luteal (Secretory) | 1 DPO to period eve (typically 12–16 days) | High progesterone plus secondary mid-luteal estradiol from corpus luteum | Ruptured follicle forms the corpus luteum; progesterone converts endometrium into a nutrient-rich secretory lining receptive to implantation (6–10 DPO). | Sustained +0.2 to +0.5 °C morning BBT shift; cervical mucus dries or thickens rapidly; possible breast tenderness, mild bloating, or mood shifts. |
What ends one cycle and starts the next depends on whether fertilisation and implantation take place. If a fertilised embryo implants in the secretory endometrium roughly 6 to 10 days after ovulation, developing trophoblast cells secrete human chorionic gonadotropin (hCG), which rescues the corpus luteum so progesterone stays elevated and menstruation does not occur. When no embryo implants, the corpus luteum has a built-in biological lifespan of roughly 12 to 16 days before regressing into scar tissue (the corpus albicans). Falling progesterone and estradiol constrict spiral arterioles in the uterine lining, triggering menstruation and resetting Cycle Day 1.
Inside the six-day fertile window: conception odds and gamete survival
Many people assume fertility is spread evenly across the middle two weeks of a cycle, or conversely that conception can only happen from intercourse on the exact day an egg is released. Landmark prospective clinical research—most notably Allen Wilcox, Clarice Weinberg, and Donna Baird's New England Journal of Medicine study tracking daily urinary hormone metabolites alongside intercourse logs—demonstrated that clinical pregnancies arise almost exclusively from intercourse during a six-day interval ending on the day of ovulation.
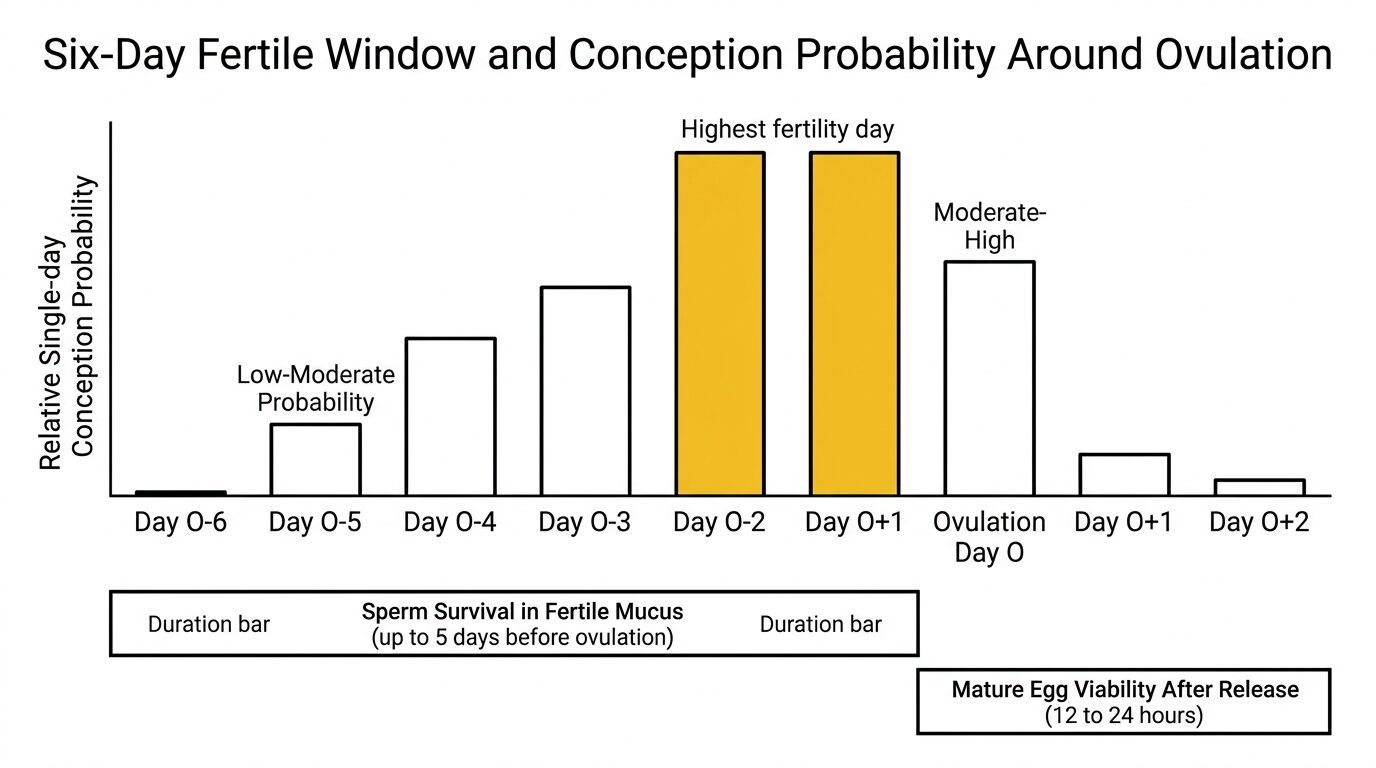
Two contrasting biological lifespans define both the width and the asymmetry of that six-day window:
- Sperm survival (up to 5 days in fertile mucus): During most of the month, the vagina is mildly acidic (pH ~3.8 to 4.5) and cervical mucus forms a dense, tangled hydrogel mesh that blocks sperm entry and limits survival to a few hours. Under rising pre-ovulatory estradiol, endocervical crypts secrete watery, alkaline mucus (pH ~7.0 to 8.5) arranged in parallel microscopic channels. Healthy sperm swim into these cervical crypts, where they are nourished and released gradually toward the uterus and fallopian tubes for up to five days (and occasionally slightly longer in exceptional cases).
- Egg viability (12 to 24 hours after ovulation): Once the ovarian follicle ruptures, the secondary oocyte is fertilisable for only 12 to 24 hours. Moreover, freshly ejaculated sperm require roughly 6 to 10 hours of physiological capacitation inside the female reproductive tract before they acquire the hyperactivated motility and acrosomal responsiveness needed to penetrate the egg's outer investments.
That capacitation requirement explains a counter-intuitive clinical finding reflected in prospective fertility cohorts: intercourse one or two days before ovulation (O-1 and O-2) consistently yields as high—or slightly higher—conception rates than intercourse on ovulation day itself. When intercourse occurs only late on Ovulation Day O, an egg released twelve hours earlier may age before capacitated sperm reach the tubal ampulla.
| Day Relative to Ovulation | Example Day (28-Day Cycle) | Approx. Single-Day Conception Probability | Fertility Tier | Biological Explanation & Planning Relevance |
|---|---|---|---|---|
| O − 6 or earlier | Day 8 or earlier | < 1% | Very low | Exceeds normal five-day sperm survival unless ovulation arrives earlier than calendar average. |
| O − 5 | Day 9 | 4% to 10% | Fertile window opens | Longest-surviving, high-motility sperm sheltered in early estrogenic cervical crypts can reach the egg five days later. |
| O − 4 | Day 10 | 11% to 16% | Moderate fertility | Increasing cervical mucus volume improves sperm reservoir survival across the four-day wait. |
| O − 3 | Day 11 | 15% to 20% | High fertility | Substantial population of viable, capacitated sperm remains active in the upper reproductive tract at egg release. |
| O − 2 | Day 12 | 25% to 30% | Peak fertility | Prime conception day; peak slippery cervical mucus facilitates rapid transport and optimal sperm freshness. |
| O − 1 | Day 13 | 28% to 33% | Peak fertility | Highest single-day conception probability across healthy young cohorts; coincides closely with the urinary LH surge. |
| Ovulation Day (O) | Day 14 | 12% to 25% | Peak / closing | Egg is released; probability is high early in the day and declines steeply hour by hour after follicle rupture. |
| O + 1 (24h buffer) | Day 15 | 0% to 3% | Transition buffer | True biological conception is near zero once 24 hours pass, but kept as a calendar buffer because late-evening ovulation spans midnight. |
For couples actively trying to conceive, reproductive medicine guidelines from NICE (CG156) and ACOG emphasise that you do not need to time intercourse to the exact hour. Having vaginal intercourse every one to two days across the fertile window (or two to three times per week starting soon after menstrual bleeding ends) captures peak fertility reliably without creating performance stress. In men with normal semen parameters, daily ejaculation over a five-to-six-day fertile stretch does not impair fertility; every-other-day spacing achieves virtually identical cumulative pregnancy rates.
Exact calendar math, Cycle Day 1 indexing, and why ovulation moves
One of the most persistent errors in casual period arithmetic is mixing up elapsed intervals with inclusive Cycle Day numbers. In clinical gynaecology, there is no "Cycle Day 0"—the first day of menstrual flow is Cycle Day 1. Consequently, moving forward to Cycle Day N means adding (N − 1) calendar days to Cycle Day 1, whereas adding the full cycle length in days lands on Cycle Day 1 of the next menstrual cycle.
This calculator uses exact local-noon calendar arithmetic (preventing one-day shifts across Daylight Saving Time transitions) according to these formulas:
Large-scale digital epidemiology confirms why subtracting the luteal phase from total cycle length is far more accurate than assuming everyone ovulates on Day 14. In a landmark 2019 study published in npj Digital Medicine (Bull et al.) analysing over 600,000 ovulatory menstrual cycles verified with basal body temperature and LH testing, only 13 per cent of cycles were exactly 28 days long. Across all participants, the average follicular phase was 16.9 days (with wide variation from 10 to more than 22 days), whereas the luteal phase clustered much more tightly around 12.4 to 14 days.
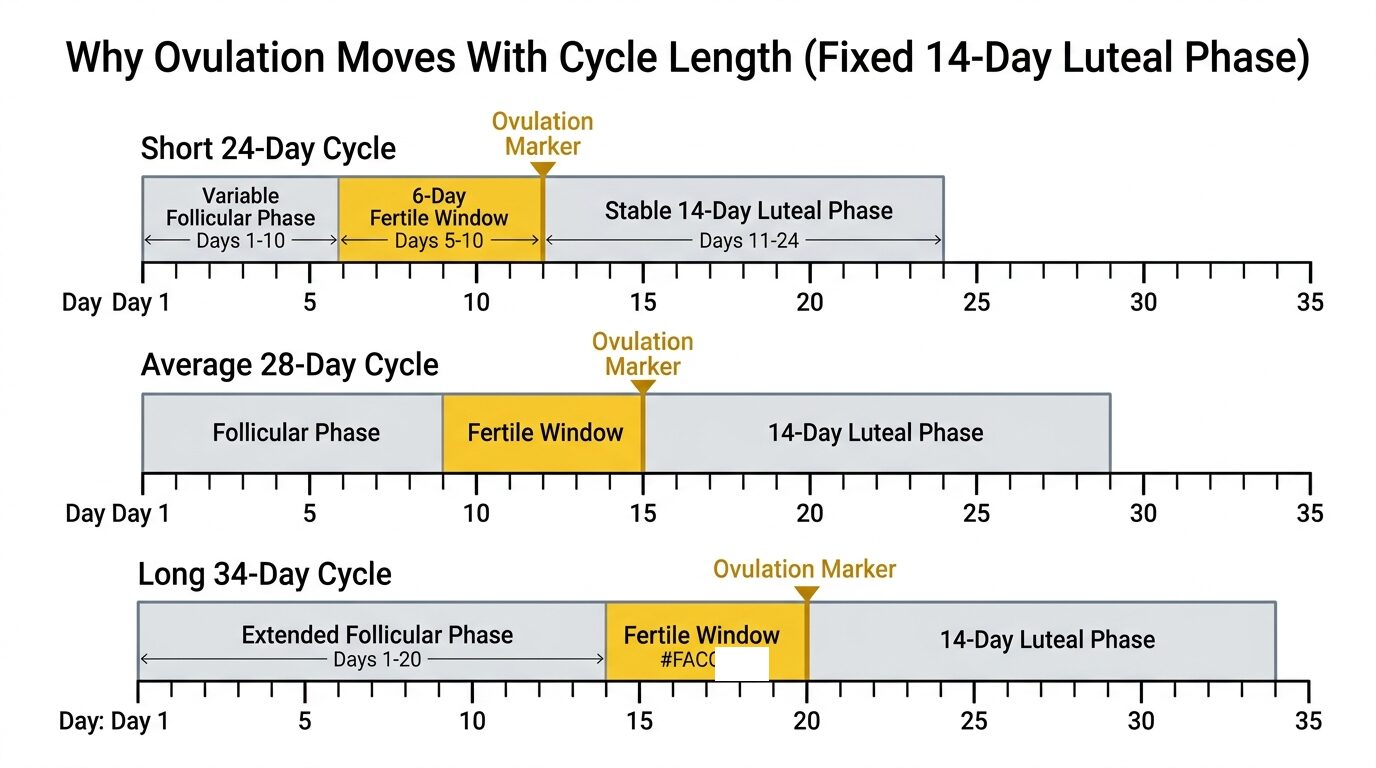
The reference matrix below illustrates how the six-day fertile window and peak days shift across six common cycle lengths when assuming a standard 14-day luteal phase, alongside how a 12-day luteal phase shifts ovulation two days later inside the very same cycle length:
| Cycle Profile | Total Cycle Length | Ovulation (14d Luteal) | 6-Day Fertile Window (14d Luteal) | Ovulation (12d Luteal) |
|---|---|---|---|---|
| Minimum normal adult cycle | 21 days | Cycle Day 7 | Days 2 to 7 | Cycle Day 9 |
| Short regular cycle | 24 days | Cycle Day 10 | Days 5 to 10 | Cycle Day 12 |
| Textbook median cycle | 28 days | Cycle Day 14 | Days 9 to 14 | Cycle Day 16 |
| Common slightly longer cycle | 31 days | Cycle Day 17 | Days 12 to 17 | Cycle Day 19 |
| Upper clinical normal cycle | 34 days | Cycle Day 20 | Days 15 to 20 | Cycle Day 22 |
| Extended / oligomenorrhoeic border | 38 days | Cycle Day 24 | Days 19 to 24 | Cycle Day 26 |
Three step-by-step worked cycle examples
Walking through three realistic user profiles—using exact dates you can enter directly into the calculator above—demonstrates how Cycle Day 1 arithmetic, bleeding duration, and luteal phase settings interact in practice.
Example 1: Standard 28-day cycle with a 5-day period and 14-day luteal phase
Suppose full menstrual flow began on 1 October 2026, your cycles consistently average 28 days, bleeding lasts 5 days, and you leave the assumed luteal phase at 14 days. Entering those four values produces an exact day-by-day partition of October:
| Cycle Stage | Cycle Day Span | Formula Step | Calendar Date(s) |
|---|---|---|---|
| Menstrual bleeding | Days 1 to 5 | LMP through LMP + 4 days | 1 Oct – 5 Oct 2026 |
| Pre-fertile follicular days | Days 6 to 8 | After period end up to Fertile Start − 1 | 6 Oct – 8 Oct 2026 |
| Clinical 6-day fertile window | Days 9 to 14 | Ovulation Date − 5 days to Ovulation Date | 9 Oct – 14 Oct 2026 |
| Peak conception days (3 days) | Days 12 to 14 | Ovulation Date − 2 days to Ovulation Date | 12 Oct – 14 Oct 2026 |
| Estimated ovulation day | Day 14 | 28 − 14 = Day 14 (1 Oct + 13 days) | 14 Oct 2026 |
| 24-hour egg-survival buffer | Day 15 (1 DPO) | Ovulation Date + 1 day | 15 Oct 2026 |
| Post-buffer luteal days | Days 16 to 28 | Ovulation Date + 2 days to Next Period − 1 | 16 Oct – 28 Oct 2026 |
| Next expected period start | Next Cycle Day 1 | 1 Oct + 28 days (four exact weeks) | 29 Oct 2026 |
Notice how every single calendar date from 1 October through 28 October maps cleanly onto Cycle Days 1 through 28 (with 15 October through 28 October comprising exactly 14 post-ovulatory luteal days), and the new menstrual period begins on 29 October 2026—exactly four Thursdays after Thursday 1 October.
Example 2: Short 23-day cycle with a 6-day period and 13-day luteal phase (bleeding overlap)
Now consider an adult in her late thirties whose cycles have shortened slightly while remaining regular: her last period began on 5 November 2026, her cycle averages 23 days, menstrual bleeding lasts 6 days, and home BBT tracking shows a 13-day luteal phase:
- Menstrual bleeding: Cycle Days 1 to 6 = 5 Nov – 10 Nov 2026.
- Estimated ovulation day: 23 − 13 = Cycle Day 10, which falls on
5 Nov + 9 days= 14 Nov 2026. - Clinical 6-day fertile window: Cycle Days 5 to 10 = 9 Nov – 14 Nov 2026 (with peak conception days on Cycle Days 8 to 10, 12 Nov – 14 Nov 2026).
- 24-hour egg buffer & remaining luteal days: Buffer on Day 11 (15 Nov 2026); lower-probability luteal calendar days on Days 12 to 23 (16 Nov – 27 Nov 2026); next expected period on 28 Nov 2026 (
5 Nov + 23 days).
Look closely at the overlap flagged in the calculator's fourth Plan Check: menstrual bleeding lasts until 10 November, while the six-day fertile window opens on 9 November (Cycle Day 5). There are zero non-fertile follicular days between menstruation and the fertile window. Someone waiting until Day 12 or 13 to start LH testing or timed intercourse would miss almost the entire fertile buildup—and someone mistakenly believing intercourse during menstrual bleeding can never cause pregnancy could conceive from intercourse on Day 5 or Day 6.
Example 3: Longer 34-day cycle with a 12-day luteal phase
Consider a person trying to conceive whose cycles regularly span 34 days, whose last period started on 10 October 2026 (lasting 5 days), and whose prior ovulation strip plus period logs revealed a 12-day luteal phase rather than 14 days:
- Estimated ovulation day: 34 − 12 = Cycle Day 22, which lands on
10 Oct + 21 days= 31 Oct 2026. - Clinical 6-day fertile window: Cycle Days 17 to 22 = 26 Oct – 31 Oct 2026, with peak fertility on 29 Oct – 31 Oct 2026.
- Next expected period start:
10 Oct + 34 days= 13 Nov 2026.
Had this person followed generic internet advice to focus on Cycle Days 11 to 15 (20 to 24 October), she would have stopped focusing on timed intercourse two full days before her six-day fertile window even opened, and a full week before actual ovulation on 31 October. Adjusting both cycle length and luteal phase prevents mistimed conception efforts and avoids ordering "Day 21 progesterone" blood tests a full day before ovulation (since a standard "Day 21" test actually means 7 days post-ovulation—which in her cycle is Cycle Day 29, 7 November!).
Confirming ovulation at home: cervical mucus, LH strips, and BBT
Calendar arithmetic tells you when ovulation is statistically expected based on past months, whereas physiological biomarkers tell you what your ovaries are doing this specific week. Pairing this calculator with one prospective sign (cervical mucus or urinary LH strips) and, if helpful, one retrospective sign (morning basal body temperature) dramatically sharpens accuracy.
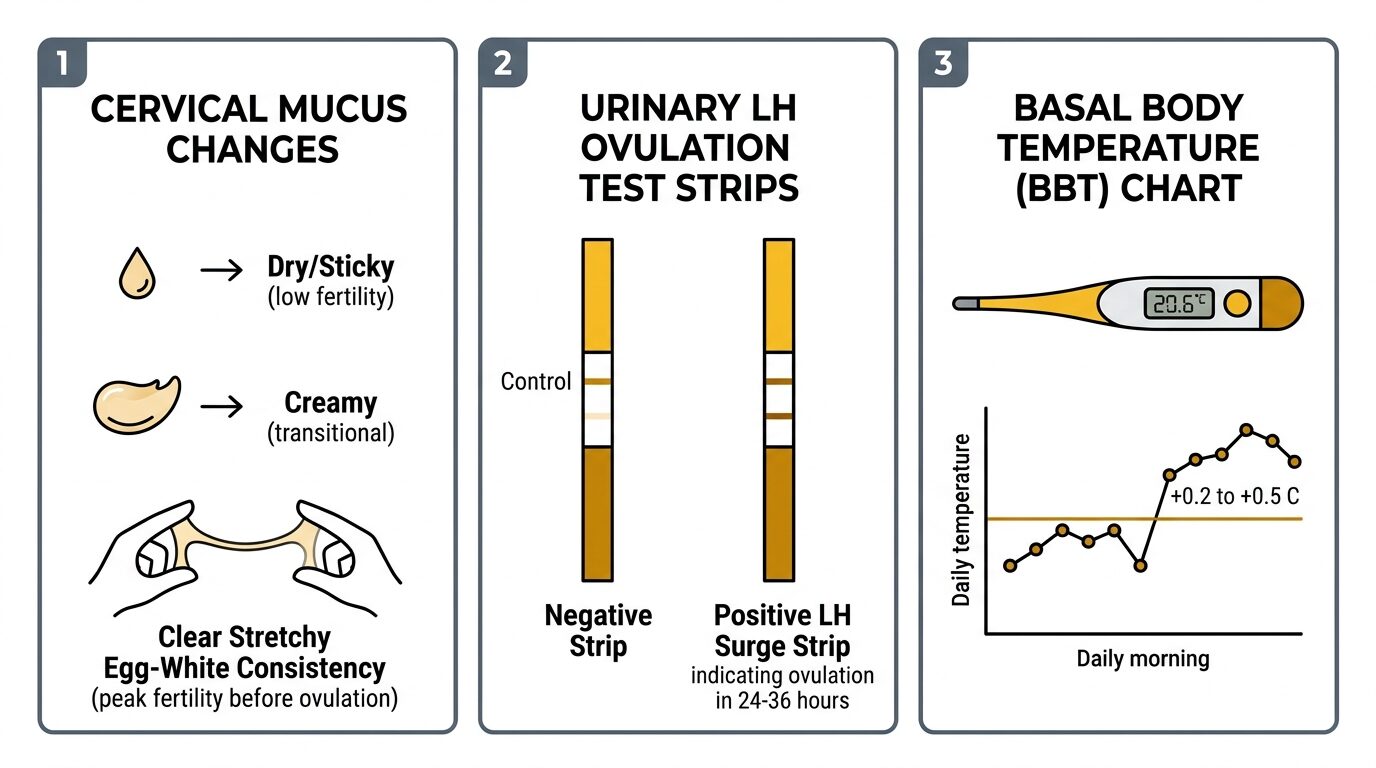
| Tracking Method | Timing Signal | What It Detects | Practical Strengths & Key Confounders |
|---|---|---|---|
| Calendar subtraction (this tool) | Advance planning estimate | Historical cycle average minus assumed luteal length | Zero cost and instant for scheduling ahead, but blind to acute stress, travel, illness, or anovulatory cycles. |
| Cervical mucus observation | Prospective (opens fertile window 3–6 days pre-ovulation) | Rising follicular estradiol stimulating endocervical fluid | Free, real-time indicator of sperm survival conditions; confounded by recent semen, vaginal lubricants, antihistamines, or vaginal infections. |
| Urinary LH ovulation predictor kits (OPKs) | Prospective (24–36 hours before follicle rupture) | Pituitary luteinising hormone surge in urine | Pinpoints peak conception days O-1 and O; can show false positives in PCOS, perimenopause, or after hCG fertility trigger injections. |
| Basal body temperature (BBT) | Retrospective (rises 1–2 days after ovulation) | Thermogenic effect of corpus luteum progesterone on hypothalamus | Confirms ovulation happened and reveals exact personal luteal length; disrupted by fever, alcohol, fragmented sleep, or night shifts. |
| Clinical serum progesterone / ultrasound | Clinical confirmation | Mid-luteal blood progesterone (~7 DPO) or serial follicle scans | Medical gold standard when investigating infertility, PCOS, or luteal insufficiency; requires timed clinic draw (~7 days before next period). |
Practical rules that prevent misreading home biomarkers
- How to read cervical mucus accurately: Check external vulvar sensation and toilet-tissue appearance before urination across the day. After menstruation, mucus typically progresses from dry or scant sticky/tacky paste, to smooth white/yellowish lotion-like cream, and finally to wet, slippery, clear-or-translucent mucus that stretches an inch or more between thumb and forefinger like raw egg white. The last day of wet, slippery, or stretchy mucus is clinically termed Peak Day and aligns within one to two days of ovulation in most cycles. Do not confuse fertile mucus with seminal fluid the day after intercourse (which dissolves rather than forming durable elastic threads) or with discharge accompanied by itching, burning, pelvic pain, or strong odour, which requires clinical testing for infection.
- Why urinary LH strips differ from pregnancy tests: Unlike home pregnancy hCG tests—where concentrated first-morning urine is always best and any distinct second line is positive—standard urinary LH test strips are only positive when the test line is as dark as or darker than the control line, because small baseline levels of LH exist in urine all month. Because pituitary LH surges frequently begin in the early morning hours and take four to six hours to filter into urine, many people catch surges most reliably testing between 11:00 and 19:00 after holding urine normally for two hours without chugging excess water beforehand. Begin testing roughly two to three days before your calculator's six-day fertile window opens.
- How to record usable basal body temperatures: Use a digital thermometer reading to two decimal places (for example
36.32 °Cor97.38 °F) rather than a coarse single-decimal fever thermometer. Measure orally or vaginally (sticking to one site all cycle) immediately upon waking—before standing, checking your phone, speaking at length, or sipping water—after at least three consecutive hours of sleep. Ovulation is confirmed retrospectively once three consecutive morning temperatures sit at least 0.2 °C (0.4 °F) above the highest of the preceding six follicular temperatures.
Irregular cycles, PCOS, thyroid shifts, postpartum, and perimenopause
Under International Federation of Gynecology and Obstetrics (FIGO) standards, adult menstrual cycles are considered clinically regular when shortest-to-longest cycle length varies by no more than 7 to 9 days across a year (up to 9 days in ages 18–25 and 42–45, and up to 7 days in ages 26–41). When cycles swing more widely—say 25 days one month, 38 the next, and 49 after that—follicular recruitment is stalling or misfiring unpredictably, and any single-number calendar calculator loses precision.
How to bracket a wider window when cycles vary moderately (6 to 9 days): Look at your last six recorded cycle lengths. Enter your shortest cycle length into the calculator first and note the start of that fertile window—that gives your earliest plausible fertile day. Then enter your longest cycle length and note the end of its fertile window plus the 24-hour buffer—that gives your latest plausible ovulatory day. Pair that wider bracket with cervical mucus or LH strips so you neither start too late nor stop too early.
Several common physiological transitions and treatable medical conditions alter or suspend normal ovulatory timing:
- Polycystic ovary syndrome (PCOS): Affecting roughly 8 to 13 per cent of reproductive-age women worldwide, PCOS frequently causes oligo-ovulation (cycles longer than 35 days) or anovulatory cycles alongside elevated androgens or polycystic ovarian morphology on ultrasound. Because baseline LH is often elevated in PCOS, urinary LH strips may show frustrating repeat near-positives; pairing cervical mucus changes with BBT confirmation—and working with a physician on evidence-based ovulation induction or metabolic care when trying to conceive—is far more effective than calendar guessing.
- Thyroid disorders and elevated prolactin: Both hypothyroidism and hyperthyroidism alter sex-hormone-binding globulin (SHBG) and GnRH pulsatility, causing heavy, light, frequent, or infrequent periods and raising miscarriage risk if untreated. Similarly, hyperprolactinaemia (from certain anti-nausea or antipsychotic medicines, pituitary microadenomas, or hypothyroidism) suppresses GnRH and shortens the luteal phase or halts ovulation altogether—often corrected rapidly once diagnosed via a simple blood panel.
- Energy availability, body weight shifts, and stress (RED-S): The hypothalamus monitors metabolic fuel closely. Rapid weight loss, chronic under-fuelling relative to training volume (Relative Energy Deficiency in Sport), eating disorders, or acute severe physiological stress can slow GnRH pulses, delaying ovulation by weeks or causing functional hypothalamic amenorrhoea. Checking whether your habitual energy intake matches your activity expenditure with the Daily Calorie Needs Calculator and Healthy Weight Range Calculator can provide helpful nutritional context alongside medical evaluation.
- Stopping hormonal contraception: Bleeding on combined pills, patches, rings, implants, injections, or hormonal IUDs is pharmacologically controlled and cannot be used to calculate natural cycle length. After stopping oral pills, patches, rings, or removing an IUD or implant, ovulation can return within two to four weeks, though two to three months of mild cycle-length adjustment ("post-pill transition") is common. After stopping depot medroxyprogesterone acetate (DMPA / Depo-Provera) injections, return of regular ovulation commonly takes 6 to 12 months from the last injection.
- Postpartum recovery and breastfeeding: Suckling-induced prolactin suppresses ovulation for a variable duration after childbirth. Critically, your first postpartum ovulation occurs roughly two weeks before your first postpartum period—meaning you can become pregnant again without ever seeing a warning period first. In clinical family planning (WHO), the Lactational Amenorrhoea Method (LAM) only provides temporary protection when all three strict criteria hold simultaneously: the infant is under six months old, breastfeeding is exclusive or nearly exclusive day and night without long feeding gaps, and zero menstrual bleeding has returned since day 56 postpartum.
- Early post-menarche adolescence and perimenopause: During the first one to three years after a teenager's first period, an immature HPO axis makes 35-to-45-day or anovulatory cycles common. Conversely, in early perimenopause (often beginning in the early-to-mid forties), rising FSH initially accelerates follicle recruitment—shortening cycles from 28 days down to 23–25 days with earlier ovulation—before skipped ovulations and 40-to-60-day intervals emerge later in the menopausal transition.
Why calendar dates are not contraception—and how FABMs differ
The calculator displays a card labelled Lower-risk calendar days (Not safe for contraception) for complete calendar transparency, so readers can see which days sit outside menstrual bleeding, the six-day fertile window, and the 24-hour post-ovulation buffer under an idealised fixed-cycle model. Treating those calendar dates as birth control is one of the commonest pathways to unintended pregnancy.
Why do raw calendar or rhythm estimates fail so frequently as contraception? Suppose your last six cycles were all 29 days long, leading the calculator to place your fertile window on Cycle Days 10 to 15. In month seven, your body recruits a dominant follicle three days faster than usual—a completely normal biological event that produces zero symptoms. You ovulate on Cycle Day 12 instead of Day 15, meaning intercourse on Cycle Day 7 or Day 8 (labelled "lower-risk" on the calendar) lands squarely inside your true fertile window. Across clinical family planning surveillance summarised by ACOG and the WHO, calendar-only rhythm methods carry typical-use unintended pregnancy rates of roughly 15 to 24 pregnancies per 100 users per year, and no fertility awareness method protects against HIV or other sexually transmitted infections (which require external or internal condoms).
If you prefer non-hormonal, behavioural pregnancy prevention, it is important to distinguish a web calendar estimator from structured, clinically validated Fertility Awareness-Based Methods (FABMs):
- Standard Days Method (CycleBeads): Validated strictly for users whose cycles always stay between 26 and 32 days inclusive, avoiding unprotected intercourse across a wide 12-day band (Cycle Days 8 through 19)—double the width of a six-day conception estimator—and switching methods if two cycles in a year fall outside 26–32 days.
- Sympto-Thermal Method (STM): Combines daily cervical mucus charting, waking basal body temperature, and strict historical calculation rules taught by an accredited instructor. Because unprotected post-ovulatory days are only opened after both mucus dry-up and three sustained elevated BBT readings confirm ovulation has genuinely finished for that month, perfect-use failure rates drop near 0.4 to 2 per cent (with typical use varying from ~2 to 13 per cent depending on consistency during fertile abstinence or barrier days).
- Modern clinical contraception: Long-acting reversible contraceptives (copper IUDs, hormonal IUDs, subdermal implants) achieve typical-use failure rates under 1 per cent per year, while combined or progestogen-only pills, injectables, patches, rings, and consistent condom use offer established clinical options tailored by a doctor, nurse, or family planning clinic. Where unprotected intercourse has already occurred during a potentially fertile interval, time-sensitive emergency contraception (copper IUD insertion, ulipristal acetate, or levonorgestrel pills) is most effective the sooner you consult a pharmacist or clinic.
Common tracking mistakes and luteal vs early pregnancy symptoms
Even diligent trackers frequently run into avoidable traps when interpreting cycle dates and two-week-wait symptoms:
- Confusing progesterone symptoms at 3 to 7 DPO with pregnancy ("symptom spotting"): Fatigue, sore breasts, mild lower abdominal cramping, heightened smell, vivid dreams, and creamy discharge during the first week after ovulation are caused by rising corpus luteum progesterone—which rises identically whether an egg was fertilised or not. Because blastocyst implantation does not even begin until 6 to 10 DPO (most commonly 8 to 10 DPO), true hCG-driven pregnancy symptoms cannot physically exist at 3 or 5 DPO.
- Testing urine hCG too early and trusting faint evaporation lines: Even sensitive home pregnancy tests (10 to 25 mIU/mL) need two to three days after implantation for urinary hCG to cross the detection threshold. Testing at 7 or 8 DPO frequently produces a discouraging false negative in cycles that turn positive at 12 to 14 DPO. Conversely, reading a plastic test cassette twenty minutes after the manufacturer's 3-to-5-minute window can reveal a colourless evaporation line that looks falsely positive.
- Using vaginal lubricants that impair sperm motility when trying to conceive: Many standard water-based personal lubricants, saliva, and olive or mineral oils have osmolality or pH profiles that slow or immobilise sperm in vitro. Couples needing lubrication during fertile-window intercourse should look specifically for isotonic, pH-balanced fertility-friendly lubricants formulated to mimic ovulatory cervical mucus (typically containing hydroxyethylcellulose or arabinogalactan).
- Treating mid-cycle pain (mittelschmerz) as an exact timestamp: Roughly one in five ovulating adults occasionally notices a dull ache or brief one-sided twinge in the lower pelvis around mid-cycle. Ultrasound correlation studies show this sensation can occur 24 to 48 hours before follicle rupture (from capsule stretching), during rupture, or afterward from minor peritoneal fluid irritation—making it a helpful general clue rather than proof that the egg has already expired.
- Scheduling a "Day 21 progesterone" blood test on Day 21 of a long or short cycle: Clinicians order mid-luteal serum progesterone to verify ovulation at peak corpus luteum output—which occurs roughly 7 days after ovulation (or 7 days before the next expected period). Cycle Day 21 is only 7 DPO in a textbook 28-day cycle! In a 35-day cycle where ovulation occurs on Day 21, drawing blood on Day 21 tests you before the corpus luteum has even formed, producing a misleadingly low result unless timed to ~Day 28 (7 DPO).
Clinical limitations, fertility timelines, and urgent warning signs
Important Medical Disclaimer: All dates, fertile windows, and interpretations provided by this calculator and guide are general educational estimates for adults. They are not a medical diagnosis, contraceptive prescription, pregnancy dating scan, or substitute for consultation with a qualified physician, obstetrician-gynaecologist, midwife, or pharmacist. Never delay or disregard professional medical care because of a calendar calculation.
Knowing what this calculator cannot detect is essential for safe health decisions. The tool cannot verify whether an ovarian follicle ruptured, measure hormone concentrations, evaluate fallopian tube patency, assess semen quality, date an established pregnancy (where first-trimester crown-rump ultrasound outperforms menstrual recall), or rule out gynaecological pathology. Use the clinical triage framework below to distinguish routine tracking variations from situations requiring timely clinic care or emergency medical attention:
| Symptom or Situation | Recommended Action Level | Clinical Rationale & What to Expect |
|---|---|---|
| Sudden or severe one-sided pelvic/abdominal pain, shoulder-tip pain, dizziness/fainting, or pain and bleeding with a positive pregnancy test | Emergency / Urgent Care Immediately | Must urgently rule out ruptured ectopic pregnancy (a life-threatening emergency when an embryo implants in a fallopian tube), ovarian torsion, or ruptured haemorrhagic ovarian cyst. |
| Heavy bleeding soaking through 1 or more pads or tampons every hour for 2+ consecutive hours, passing large clots with lightheadedness, or shortness of breath | Emergency / Urgent Care Immediately | Acute heavy menstrual or early-pregnancy haemorrhage can cause rapid blood loss and haemodynamic instability requiring immediate medical stabilisation. |
| High fever, chills, severe bilateral pelvic tenderness, or purulent/foul-smelling vaginal discharge (especially with recent tampon/cup use or procedure) | Emergency / Urgent Same-Day Care | Requires urgent evaluation and treatment for acute pelvic inflammatory disease (PID), endometritis, or menstrual toxic shock syndrome (TSS). |
| Cycles consistently < 21 days or > 35–38 days, no period for 90+ days (non-pregnant), bleeding > 7–8 days, or bleeding between periods or after intercourse | Prompt Routine Gynaecology / GP Visit | Evaluates treatable causes including PCOS, thyroid dysfunction, uterine fibroids, endometrial polyps, cervical pathology (essential to screen post-coital bleeding), or coagulation disorders. |
| Severe period pain (dysmenorrhoea) causing missed work or classes, painful deep intercourse, or cyclical bowel/bladder pain | Prompt Routine Gynaecology Visit | Debilitating menstrual pain is not something you must simply endure; clinicians evaluate for endometriosis, adenomyosis, or fibroids. |
| Actively trying to conceive without pregnancy: 12 months (if age < 35), 6 months (if age 35+), or immediately with known cycle irregularity | Scheduled Fertility Assessment (Couple) | Follows NICE CG156, ACOG, and WHO guidelines for timely baseline evaluation of ovulatory function, semen analysis, ovarian reserve, and tubal health. |
If you are planning a pregnancy in the coming months, international obstetric guidelines (WHO, NICE, ACOG) also recommend starting a daily 400 microgram (0.4 mg) folic acid supplement at least one to three months before conception (continuing through the first twelve weeks of pregnancy) to substantially lower the risk of fetal neural tube defects—asking your doctor or pharmacist first if you have diabetes, epilepsy medications, malabsorption, or a family history of neural tube defects, where a higher 4 to 5 milligram prescription dose is typically advised.
Authoritative clinical sources and guidelines
- American College of Obstetricians and Gynecologists (ACOG). Fertility Awareness-Based Methods of Family Planning (FAQ024 & Clinical Guidance). acog.org
- Wilcox AJ, Weinberg CR, Baird DD. Timing of sexual intercourse in relation to ovulation: effects on the probability of conception, survival of the pregnancy, and sex of the baby. New England Journal of Medicine, 1995;333(23):1517–1521. pubmed.ncbi.nlm.nih.gov/7477195
- Bull JR, Rowland SP, Scherwitzl EB, Scherwitzl R, Danielsson KG, Harper J. Real-world menstrual cycle characteristics of more than 600,000 menstrual cycles. npj Digital Medicine, 2019;2:83. pubmed.ncbi.nlm.nih.gov/31482137
- National Institute for Health and Care Excellence (NICE). Fertility problems: assessment and treatment (Clinical Guideline CG156). nice.org.uk/guidance/cg156
- World Health Organization (WHO) & Johns Hopkins Bloomberg School of Public Health. Family Planning: A Global Handbook for Providers (4th ed., updated edition). who.int
- Munro MG, Critchley HOD, Fraser IS; FIGO Menstrual Disorders Committee. The two FIGO systems for normal and abnormal uterine bleeding symptoms and classification of causes of abnormal uterine bleeding in the reproductive years: 2018 revisions. International Journal of Gynecology & Obstetrics, 2018;143(3):393–408. pubmed.ncbi.nlm.nih.gov/30198563
- Practice Committee of the American Society for Reproductive Medicine (ASRM). Optimizing natural fertility: a committee opinion. Fertility and Sterility, 2022;117(1):53–63. asrm.org